

The Effect of Uterine Fibroids on Fertility
Uterine fibroids-noncancerous growths in the uterus-are very common, affecting about one in three women during their reproductive years. For many, fibroids cause no symptoms and don’t interfere with the ability to get pregnant. But for others, these growths can make it harder to conceive or carry a pregnancy to term. If you’re trying to get pregnant and have been diagnosed with fibroids, you may be wondering what this means for your fertility or whether treatments like IVF will still work. In this blog, we’ll explain how fibroids can impact fertility, how they might affect IVF success, and when surgery or other treatments may be recommended.
What Are Uterine Fibroids?
Fibroids are made of smooth muscle and fibrous tissue. They can be tiny-smaller than a pea-or grow as large as a melon. Some women may have just one, while others develop multiple fibroids. Where they grow inside or around the uterus makes a big difference in how they affect your body and fertility.
Here are the main types:
- Submucosal fibroids: These grow just underneath the lining of the uterus and may push into the uterine cavity. They’re the most likely to interfere with pregnancy.
- Intramural fibroids: Found in the muscular wall of the uterus. Depending on size, they can affect the shape of the uterus. They may also affect implantation if close to the uterine lining.
- Subserosal fibroids: Grow on the outer surface of the uterus. These usually don’t affect fertility unless they’re very large.
- Pedunculated fibroids: Attached to the uterus by a thin stalk, either inside or outside the uterus.
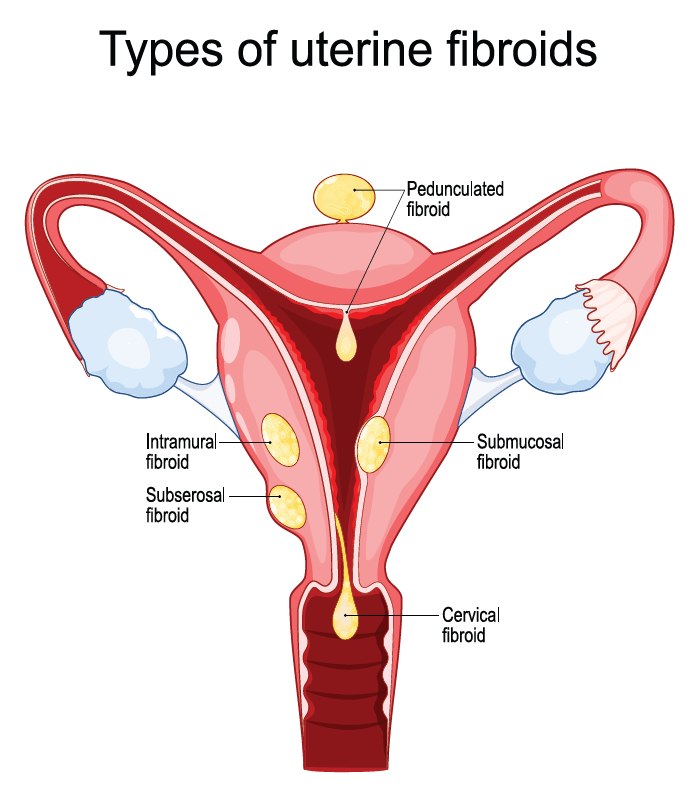
Source: ASRM
How Can Fibroids Affect Fertility?
While fibroids do not universally impair fertility, they can disrupt reproductive success through several distinct mechanisms:
- Distorting the Uterine Architecture: Submucosal fibroids alter cavity contours, compromising the physical space and structural support required for proper embryo implantation.
- Obstructing Tubal Ostia: Large intramural or subserosal growths can compress or block the fallopian tubes, preventing gamete transport and fertilization.
- Compromising Endometrial Blood Flow: Fibroids can alter local vascular perfusion to the uterine lining, hindering optimal endometrial receptivity and early placental development.
- Altering the Molecular Environment: Fibroids can induce localized inflammatory responses within the myometrium and endometrium, creating a less hospitable environment for embryonic growth.
Do Fibroids Affect IVF Success?
For individuals pursuing in vitro fertilization (IVF), the presence and location of fibroids can significantly influence clinical outcomes:
- Submucosal Fibroids: Consistently associated with reduced IVF success; surgical correction generally restores pregnancy and live-birth rates.
- Intramural Fibroids: Those exceeding 5 cm or distorting the endometrial cavity may depress implantation rates, though clinical consensus varies.
- Subserosal Fibroids: Generally exert negligible impact on IVF metrics unless exceptionally large or multifocal.
Pre-IVF intervention can optimize cavity contours, though sequencing requires careful clinical tailoring. For patients of advanced maternal age or with diminished ovarian reserve, physicians often prioritize banking euploid embryos via IVF prior to surgical correction to preserve precious time. Conversely, if fibroids impede safe transvaginal access to the ovaries during egg retrieval, a myomectomy must precede ovarian stimulation. Your specialist will formulate an individualized roadmap tailored to your specific diagnostic profile.
When Is Surgery for Fibroids Recommended?
Surgical intervention is indicated when fibroids compromise fertility, induce abnormal uterine bleeding, cause pelvic pain, or contribute to recurrent pregnancy loss. The gold standard procedure is a myomectomy, which excises the fibroid tissue while preserving the integrity and reproductive potential of the uterus.
Surgical methodology is guided primarily by anatomical location:
- Hysteroscopy: Intracavitary submucosal fibroids are typically excised vaginally via a specialized hysteroscope without abdominal incisions, allowing for rapid recovery.
- Laparoscopy or Laparotomy: Intramural and subserosal lesions often require minimally invasive laparoscopy or open abdominal approaches depending on size, count, and overall surgical complexity.
Surgical management is typically recommended under specific clinical criteria:
- Presence of submucosal fibroids distorting the endometrial cavity
- Intramural fibroids measuring larger than 4 cm
- History of recurrent implantation failure or multiple miscarriages
- Unexplained failed prior IVF cycles where fibroids are suspected contributors
Treatment decisions carefully weigh restorative benefits against surgical risks, such as postoperative adhesions or uterine scarring. Asymptomatic or small fibroids that leave the uterine cavity undisturbed are frequently monitored rather than resected.
Are There Non-Surgical Options?
While non-surgical modalities exist, many are poorly suited for patients actively pursuing conception:
- Uterine Fibroid Embolization (UFE): A minimally invasive procedure that restricts blood supply to infarct and shrink fibroids. Because it can compromise overall uterine perfusion and adversely impact ovarian reserve, UFE is generally contraindicated for patients desiring future pregnancy.
- Medical Therapy: Pharmacological agents, such as gonadotropin-releasing hormone (GnRH) agonists or antagonists, temporarily reduce fibroid volume. While occasionally deployed prior to surgery or egg retrieval to optimize surgical fields or uterine access, they do not serve as permanent fertility-restoring treatments.
What If I Get Pregnant With Fibroids?
The vast majority of women with fibroids experience healthy, successful pregnancies. However, large or placentally adjacent fibroids can elevate specific obstetric risks, including:
- First-trimester or recurrent miscarriage
- Preterm labor and premature rupture of membranes
- Placental abruption or abnormal placentation
- Intrauterine growth restriction (fetal growth restriction)
- Increased likelihood of cesarean delivery
When fibroids are present, your obstetrician or reproductive endocrinologist will implement enhanced surveillance protocols, utilizing serial sonograms to monitor structural dimensions and clinical positioning throughout gestation.
A Personalized Path to Parenthood
A diagnosis of uterine fibroids does not preclude a successful family-building journey. Achieving optimal outcomes relies on an individualized diagnostic and therapeutic strategy. Comprehensive evaluations-including advanced imaging modalities such as saline infusion sonography (sonohysterogram) or pelvic MRI-allow specialists to map fibroid topography against your specific reproductive goals and timeline. Whether targeted myomectomy or uncompromised IVF protocols offer the ideal pathway, a precise diagnosis ensures you move forward with clarity and confidence.